Air Force General Surgery Physician Assistant: The 42G Surgical Path
An Air Force general surgery physician assistant supports care before an operation, assists during it within granted privileges, and follows patients through recovery. The specialty is suffix C within the 42G PA field, earned after the required PA qualification and accepted surgical preparation.
The job differs from becoming a surgeon: the educational route, operative responsibilities, and clinical authority are different. An applicant should establish the actual training and billet opportunity before treating the specialty as an accession offer.
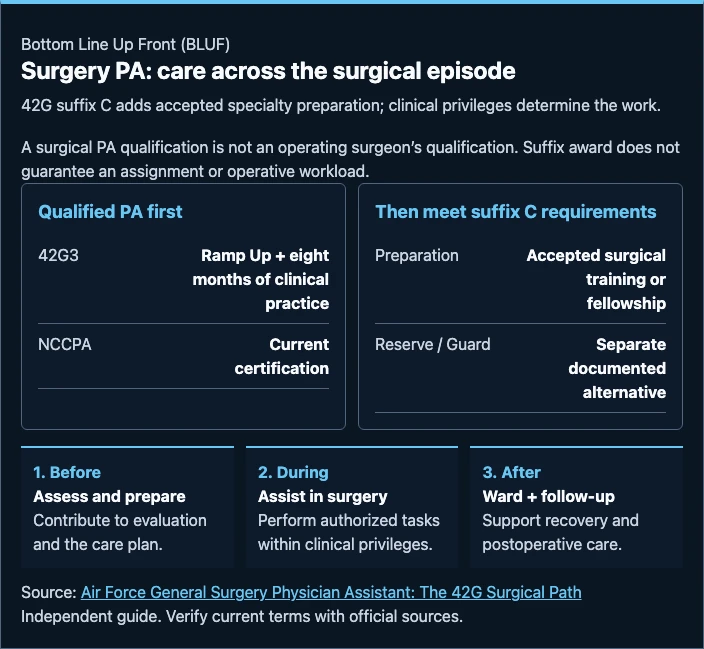
A surgical PA qualification is not an operating surgeon’s qualification. Suffix award does not guarantee an assignment or operative workload.
Qualified PA first
- 42G3
- Ramp Up + eight months of clinical practice
- NCCPA
- Current certification
Then meet suffix C requirements
- Preparation
- Accepted surgical training or fellowship
- Reserve / Guard
- Separate documented alternative
- BeforeAssess and prepareContribute to evaluation and the care plan.
- DuringAssist in surgeryPerform authorized tasks within clinical privileges.
- AfterWard + follow-upSupport recovery and postoperative care.
Source: Air Force General Surgery Physician Assistant: The 42G Surgical Path
Independent guide. Verify current terms with official sources.
On this page
Job Role and Responsibilities
Air Force general surgery physician assistants (AFSC 42G, suffix C) care for surgical patients across the whole arc of an operation. They assess patients before surgery, first-assist in the operating room, manage wounds, drains and lines afterwards, and run the follow-up clinic. The job belongs to the 42G physician assistant field and adds operative and perioperative practice to general PA work.
The suffix is the part that matters for planning. A PA does not choose surgery at accession. The Air Force awards suffix C after the officer reaches the qualified PA level and completes the specialty preparation the Surgeon General accepts.
The Three Parts of the Work
Perioperative care follows the patient through three stages, within the PA’s granted clinical privileges:
- Before surgery: Take the history, review imaging and labs, document risk factors, and check consent and pre-op orders.
- During surgery: Retract, suction, tie, cut, and close under the surgeon’s direction, keeping the field moving so the surgeon can concentrate on the operative work.
- After surgery: Write notes, manage pain and fluids, change dressings, remove drains, and assess readiness for discharge.
That last part carries the most weight in a busy service. Surgical patients leave the operating room and land on a ward, and somebody has to see them every day. A PA who catches a wound infection on the second morning, or a patient whose pain is out of proportion to the operation, changes the outcome.
What the PA Does Not Do
The PA is not the operating surgeon. The surgeon plans the operation, carries the responsibility for the technical result, and holds the privileges that go with it. The PA works within granted clinical privileges and the operative team’s responsibilities.
The directory describes autonomous or collaborative PA care and separately requires clinical privileges; it does not impose one supervision arrangement on every PA duty.
This boundary is not a comment on skill. Operating-room responsibilities depend on the procedure, the facility’s privileges, and the clinical team; this is not a statement that every jurisdiction uses the same practice law. A PA with ten years of operating experience still works under a surgeon’s authority in the room.
Specific Roles and Designations
The 42G field tracks skill and specialty in one code.
| Code | Meaning |
|---|---|
| 42G1 | Entry level and student |
| 42G3 | Qualified physician assistant |
| 42G4 | Staff |
| 42G3A | Orthopedics |
| 42G3B | Otolaryngology |
| 42G3C | General surgery |
| 42G3E | Emergency medicine |
| 42G3N | Psychiatry |
| 42G3P | Aeromedical |
Suffix C sits alongside the other surgical and clinical specialties in the same field, and each one has its own award rule. The 42G Physician Assistant profile covers the shared accession and pay rules for all of them.
Mission Contribution
Surgical capability is what lets a medical unit treat the injuries that kill quickly. A deployed surgical team can open an abdomen, control bleeding, and stabilize a patient for movement to a larger hospital. The PA is part of that team, and the team is smaller than its civilian equivalent, so each member covers more ground.
In garrison, the contribution is volume and continuity. PAs can provide continuity across the clinic, ward, and operating room within the facility’s staffing and privileges. That is also how the Air Force keeps surgical skills current between deployments.
Technology, Equipment, and Systems
The tools are those of a modern operating suite: electrocautery, laparoscopic towers, staplers, and instrument sets for open and minimally invasive cases. PAs document in the military health record, order imaging and labs, and manage drains, catheters, and feeding tubes on the ward. Deployed, the same work happens with a smaller footprint and less imaging, which changes what can be done on site.
Salary and Benefits
A general surgery PA is paid as a 42G officer. Working in an operating room does not by itself establish a bonus entitlement; compare the actual terms of the accession or retention agreement.
| Rank | Pay Grade | Years of Service | Monthly Base Pay | Annual Base Pay |
|---|---|---|---|---|
| Second Lieutenant (2d Lt) | O-1 | 2 or less | $4,150 | $49,802 |
| First Lieutenant (1st Lt) | O-2 | Over 2 | $5,446 | $65,354 |
| Captain (Capt) | O-3 | Over 4 | $7,383 | $88,592 |
| Major (Maj) | O-4 | Over 10 | $9,420 | $113,040 |
Source: DFAS 2026 pay tables. Figures reflect the 2026 pay raise.
Base pay follows rank and years. The food allowance for officers is $328.48 a month, and housing pay varies by base, rank and family status.
Special Pays
Medical special pays have their own eligibility, certification, agreement, and effective-period rules. Holding a PA certification or a clinical suffix does not establish entitlement to every payment shown on a health-professions pay table.
Before comparing an accession offer with civilian work, request the current written Air Force terms for board certification pay, incentive pay, and any bonus. Identify the agreement length, additional service obligation, and whether payments can be combined; do not budget from an undated range or another profession’s schedule.
What the Pay Comparison Actually Says
Civilian offers vary by employer, location, and experience. Compare the complete military package, including allowances, healthcare eligibility, and the applicable retirement plan, against an actual civilian offer.
Service length changes the retirement comparison. Use the applicable plan and eligibility rules rather than assuming a full military pension is part of every accession offer.
Qualifications and Eligibility
The 42G Floor
The officer classification directory defines 42G qualification and suffix award. The Air Force PA recruiting page supplies the public accession overview and currently lists 8.5 weeks of officer training at Maxwell; confirm the course allocated to your program.
Every PA in the field meets the same baseline before a suffix enters the picture. The classification directory requires:
- A master’s degree from a PA program accredited by the Accreditation Review Commission on Education for the Physician Assistant (ARC-PA).
- At least 12 months of hands-on clinical rotations in the final year.
- A commissioning program to reach the qualified skill level.
- Initial certification through the National Commission on Certification of Physician Assistants (NCCPA) exam within 12 months of graduation.
The directory strongly encourages a state PA license and requires current NCCPA certification for the qualified level. Certification and clinical privileges must be maintained; a lapse requires action under the applicable personnel and credentialing rules.
Two Ways In
| Route | Entry grade | What it requires |
|---|---|---|
| Health Professions Scholarship Program | O-1 | Enrolled in an accredited PA master’s program, scholarship support, Commissioned Officer Training during the program |
| Direct accession | O-2 | Completed master’s degree and current NCCPA certification before entry on active duty |
Reserve and Air National Guard units also take PAs by direct accession against a unit vacancy. The parent profile covers both routes in detail, including the service commitment each one carries.
How Suffix C Is Awarded
This is the part a prospective surgical PA needs to understand before applying. The classification directory awards the surgical suffix only after two conditions are met. The officer must hold the qualified 42G3 level, and the officer must complete a suffix-specific training program or fellowship acceptable to the Surgeon General.
The qualified level itself is not automatic at commissioning. A new PA completes the 42G Ramp Up, then eight months of clinical practice, and holds current certification before the 42G3 is awarded. Surgery comes after that, not instead of it.
There is a second route for Reserve and Guard PAs who already practice in the specialty. In place of an approved fellowship, the directory accepts current and continuous practice in the specialty, an NCCPA Certificate of Added Qualifications, an annual attestation from a civilian department chair covering case logs and performance, and annual approval by the Consultant to the Surgeon General for PA Specialties.
What That Means for a New Applicant
A PA student cannot apply for the surgical suffix. A certified PA with surgical experience cannot be promised it at accession either. The suffix is earned inside the Air Force, after the qualified level, and the fellowship list and selection timing change from year to year.
Ask a health recruiter two questions before signing: whether the current accession can lead to a surgical billet at all, and how the specialty fellowship selects officers that year. The answers decide whether the plan is realistic.
Test Requirements
PA certification and clinical qualifications are the relevant professional preparation here. Do not assume that attending an officer commissioning course creates an AFOQT requirement.
Ask a health-professions recruiter which examinations apply to your accession program, and confirm that answer before buying test preparation. This page does not recommend a paid preparation product because no relevant approved offer has been established for the clinical route described.
Work Environment
A Surgical Day
Surgical services run on a block schedule. The operating room belongs to a service for a set number of hours, and the cases fill that block. A PA on a surgical service splits the week between the operating room, the ward, and clinic, and the split depends on how the service is staffed that month.
An operating room day starts early. The team reviews the list, confirms the site and the consent, and checks the imaging is on the screen. Cases run back to back, and a long one pushes everything after it.
The PA stays for the whole list, not one case.
The Team in the Room
A surgical case needs more people than the two at the table. Anesthesia owns the airway and the physiology. Scrub techs and circulating nurses own the instruments and the count.
The surgeon owns the operation. The PA works between the surgeon and the rest of the room, and the job is as much coordination as technique.
That coordination is why surgical PAs tend to be calm under time pressure. The room has a rhythm, and someone who breaks it creates risk. A PA who anticipates the next instrument or the next step keeps the case moving without being told.
Ward and Clinic
The ward rounds happen before the operating room, and they are the part of the job that never stops. A PA checks the post-operative patients, reviews the labs, looks at the wounds, and decides what changes before the next case. Clinic fills the gaps with new referrals, post-operative checks, and minor procedures.
This is also where the job differs most from emergency medicine. The emergency PA sees a patient once and hands them on. The surgical PA follows the same patient from the decision to operate through recovery, which means living with the result.
Staff and Command
Surgical services sit inside a medical group, and the PA works for a flight or a department. Early on the work is clinical. As the PA promotes, the job adds rosters, privileging files, quality reviews, and training plans for medics and junior PAs.
A senior PA may run the day-to-day operation of a clinic while the surgeon runs the service.
Training and Skill Development
The Path in Order
| Stage | Where | Length | Focus |
|---|---|---|---|
| Officer commissioning course | Maxwell AFB, Alabama | Recruiting page lists 8.5 weeks; confirm accession allocation | Officership, customs, leadership basics |
| 42G Ramp Up | First duty station | Not stated in the classification directory | Supervised clinical practice before the qualified level is awarded |
| Qualified 42G3 | First duty station | Eight months of clinical practice after Ramp Up | Qualified PA work with current certification |
| Surgical suffix training or fellowship | Assigned by the Air Force | Program-specific | Operative and perioperative practice acceptable to the Surgeon General |
| Surgical assignment | Gaining medical treatment facility | Ongoing | Operating room, ward, and clinic practice |
The lengths that are not printed in the directory are the ones that vary most. The fellowship length depends on the program, and the Ramp Up is a period of supervised practice rather than a fixed course.
What the Fellowship Adds
PAs enter fellowships with different clinical backgrounds, so prior operating-room experience should not be assumed either present or absent. The fellowship teaches the operative part: instrument handling, wound closure, assisting technique, and the judgment to know when a case is beyond the plan. It also teaches the perioperative part that PAs underestimate, which is managing a ward of post-operative patients who are all recovering at different rates.
The subspecialty route into a 42G1X fellowship is separate and stricter. It requires a qualified 42G3 with at least 36 months of clinical experience at the start of the program; that requirement does not specify that every month must be in general medicine.
Professional Military Education
Squadron Officer School comes early, usually as a captain, in residence or by correspondence. Air Command and Staff College follows for majors selected for it, and Air War College serves lieutenant colonels and colonels. None of it involves patients, and all of it counts at promotion boards.
Keeping the Credential
Certification is not a one-time event. PAs recertify on a cycle and complete continuing education throughout. The Air Force ties continued service to holding both the certification and the clinical privileges that go with it, so a lapse is a career event rather than paperwork.
Career Progression and Advancement
Promotion Timeline
| Rank | Career context, not a promotion date | Typical duties |
|---|---|---|
| O-1, second lieutenant | Entry grade for scholarship students | Training and supervised practice |
| O-2, first lieutenant | Entry grade for qualified PAs | General clinic work, building the record |
| O-3, captain | Eligibility and performance rules apply | Independent practice, surgical fellowship, Squadron Officer School |
| O-4, major | Board selected | Surgical service leadership, staff work |
| O-5, lieutenant colonel | Board selected | Flight or squadron leadership, senior clinical roles |
| O-6, colonel | Board selected, few positions | Medical group leadership |
This Ladder Is Not a Surgeon’s Ladder
The comparison people actually want is the one between the two jobs, and the honest version starts with time.
A surgeon spends four years in medical school and then five or more years in a surgical residency before practicing independently. A PA spends about two years in a master’s program and starts supervised practice immediately. The surgeon enters the Air Force as a physician at a higher grade with credit for that training.
The PA enters lower and earns clinical authority through practice and specialty preparation.
The result is two different careers with different ceilings. A PA can lead a clinic, a flight, or a squadron, and can hold senior clinical and staff roles. A PA cannot become the operating surgeon, and no amount of Air Force experience changes the credential behind that.
Broadening
PAs can pursue the other 42G suffixes, and the 42G1X fellowship route broadens a career inside the same field. Wider assignments include recruiting, instructor duty, joint staff, and fellowships. A PA who wants to command should say so early, because the file that wins a board is built years before the board meets.
Physical Demands and Medical Evaluations
Fitness Assessment
Officers take the general fitness test. The current assessment scores a run or shuttle run, strength and core events, and a waist-to-height measure, with 75 points as the passing total and a minimum on each event chosen.
| General test, under age 25 | Male | Female |
|---|---|---|
| Minimum satisfactory total | 75 points | 75 points |
| Event minimums | Meet each chosen event’s chart minimum | Meet each chosen event’s chart minimum |
| Failure despite 75 total | A missed event minimum can make the result unsatisfactory | A missed event minimum can make the result unsatisfactory |
The current age and sex score sheets were not checked for this page. Use the official charts on the Air Force fitness page.
Standing, Lifting, and the Operating Room
A long surgical list is physical work. A PA stands for hours, holds retractors against tension, and moves patients and equipment. Back and shoulder strain is common in surgical practice, and the fix is positioning and help rather than endurance.
The job also carries the ordinary clinical exposure risks: bloodborne pathogens, needle sticks, and sharps during closure. Vaccination, eye protection, and safe sharps handling are the controls, and they are not optional in a military treatment facility.
Medical Standards
A surgical PA does not need a flight physical. Entry requires the health standards for new officers, and clinical work requires privileges granted under the Defense Health Agency quality rule the classification directory names. A PA in a non-clinical assignment must still be able to hold those privileges when the next assignment returns them to patient care.
Deployment and Duty Stations
What Surgical Care Looks Like Forward
Deployed medical care is built in layers, and surgery sits near the front of them. An expeditionary medical support unit brings hospital-level capability to an austere location, and the surgical team inside it stabilizes casualties before aeromedical evacuation moves them to a larger facility. The 44X Medical Officer page describes how that structure works for physicians.
A surgical PA in that setting does the same job with less around it. Imaging is limited and blood products are limited, so the examination carries more of the decision and a study that cannot be done is not part of the plan.
Tempo
Deployment tempo follows the unit, not the specialty. A PA assigned to a surgical unit that rotates regularly deploys more often than one at a large stateside medical center. The Air Force does not publish deployment rates by specialty, so any number quoted for this field is an estimate rather than a record.
Short trips are part of the work too. Surgical teams travel for exercises, for humanitarian missions, and to support operations that need a surgical capability without a full deployment.
Duty Stations
Surgical services exist at the larger military treatment facilities and at some smaller ones with a surgical mission. The Air Force also assigns PAs to staff and training positions where the operating room is a memory rather than a daily routine.
Assignments run through the officer assignment system, with preference worksheets and the needs of the Air Force deciding the outcome. A PA who wants to stay surgical should say so at every assignment cycle, because a non-surgical tour taken for career reasons can last longer than intended.
Risk, Safety, and Legal Considerations
Clinical Risk
Surgical practice concentrates risk. A retained instrument, a missed infection, or a patient sent home too early are the events that end careers and harm people. The controls are the ones every surgical service uses: counts before closure, structured handoffs, and a second set of eyes on anything that looks wrong.
A PA’s specific risk is the boundary. Working inside granted privileges and escalating when a case exceeds them is the professional obligation, and it is also the legal one. A PA who improvises outside the scope creates liability for the officer, the surgeon, and the command.
Supervision and Privileges
The classification directory ties continued service to holding privileges under the Defense Health Agency quality rule. The facility determines the PA’s authorized scope and required professional arrangements. A lapse in certification or privileges requires action under the applicable credentialing and personnel rules.
Supervision in surgery is not constant oversight. A competent PA works with the surgeon available rather than watching, and the arrangement is defined by the hospital’s privileging decision rather than by the day’s schedule.
Officer Accountability
A PA is an officer first. That carries command responsibility over assigned personnel, duties under military law, and the standards that apply to equal opportunity and climate. Clinical performance and command responsibilities are assessed through their applicable processes; neither should be reduced to a universal claim about how every adverse event affects a career.
Surgical officers also sit near purchasing and contracting decisions, which brings conflict-of-interest rules into ordinary work. Gifts from vendors and relationships with device representatives are governed, and the rules apply to PAs as much as to surgeons.
Impact on Family and Personal Life
The Schedule
Surgical hours are early and unpredictable. A list that starts at seven can run past dinner, and an add-on case can appear at any point in the day. Call exists in most surgical services, though how much depends on the facility and the staffing.
That rhythm is harder on a family than a clinic schedule, and it is one of the reasons PAs who want predictable hours choose primary care instead. Whether that trade suits an applicant depends on their interest in operative care and tolerance for an unpredictable schedule.
Moves
Permanent change of station timing varies by assignment and component. Each one resets schools, jobs, and a spouse’s career. Surgical PAs move between a small number of facilities with surgical missions, which narrows the list of possible locations and can make preferences harder to honor.
Deployment and Absence
A deployed surgical PA is gone for months, and the service at home is short while the officer is away. Ask the installation support center about family readiness services, unit spouse support, and military family life counseling available locally. The practical advice is to use them before a deployment rather than during one.
Reserve and Air National Guard
Availability
The 42G field exists in the Air Force Reserve and the Air National Guard, and both components take PAs by direct accession against a unit vacancy. Surgical work is one of the skills a unit may need, and a civilian surgical PA brings the experience with them.
The Alternative Route to the Suffix
This is the part of the specialty where the Reserve and Guard differ most from active duty, and it is worth knowing before assuming the fellowship is the only path.
For Reserve and Guard PAs, the classification directory accepts an alternative to an approved fellowship. It requires current and continuous practice in the specialty, an NCCPA Certificate of Added Qualifications, an annual attestation from a civilian department chair covering case logs and performance, and annual approval by the Consultant to the Surgeon General for PA Specialties.
That route suits a PA who already assists in surgery in civilian practice and joins a unit that needs the skill. It does not shorten the 42G3 requirement, and it does not guarantee a surgical billet. It changes how the specialty is documented rather than how it is earned.
Commitment and Pay
The standard commitment is one unit training assembly a month plus two weeks of annual tour, with additional clinical days in some units to keep skills and privileges current.
| Component | Grade | Approximate monthly drill pay, four periods |
|---|---|---|
| Air Force Reserve or Air National Guard | O-3, over four years | $984.36 for four drill periods |
The 2026 DFAS officer drill pay table lists $246.09 for one paid drill period at that grade and service point. Four periods total $984.36 before deductions. Annual training and active orders follow separate pay rules, and drill pay does not include every active-duty allowance.
Benefits Compared
| Feature | Active duty | Air Force Reserve | Air National Guard |
|---|---|---|---|
| Pay | Full base pay and allowances | Drill pay unless mobilized | Drill pay unless mobilized |
| Healthcare | TRICARE Prime at no cost | TRICARE Reserve Select with premiums | TRICARE Reserve Select or state coverage |
| Education | GI Bill and tuition assistance | Partial GI Bill eligibility and tuition assistance | State tuition waivers vary, and tuition assistance is available |
| Retirement | Applicable retirement plan and eligibility | Points-based reserve retirement | Points-based reserve retirement |
| Surgical practice | Full-time operating room access | Depends on the unit and its clinical agreement | Depends on the unit and its clinical agreement |
| Special pays | Subject to eligibility and agreements | Component and agreement rules apply | Component and agreement rules apply |
The clinical row is the one that decides the choice for a surgical PA. Keeping operative skills sharp needs volume, and a unit without a clinical affiliation may not provide it. Ask that question before signing, not after.
Post-Service Opportunities
What the Experience Is Worth
A surgical PA can document first-assist hours, ward management, and perioperative responsibilities when applying for civilian work. The strength of that record depends on the actual assignment and case volume; military service does not establish that civilian-trained PAs lack comparable experience.
Surgical practices, hospital systems, and the Department of Veterans Affairs hire military PAs directly. Military experience can support an application, but a new employer still verifies credentials and grants its own privileges. The Transition Assistance Program and Hiring Our Heroes are the usual first stops in the year before separation.
Civilian Pay
| Civilian role | Median annual pay | Outlook, 2025 to 2035 |
|---|---|---|
| Physician assistant | $135,880 (May 2025) | 21 percent growth, much faster than average |
This is an occupation-wide median, not a salary estimate for this specialty or an offer to a separating officer. Specialty, location, experience, and the employer’s requirements can change an actual offer.
Credentials and Further Study
Certification remains subject to renewal, and civilian practice requires the applicable state license. A surgical PA who wants to teach or lead can use the Post-9/11 GI Bill for a graduate degree, and the Air Force funds some graduate education through the Air Force Institute of Technology while the officer is serving.
Is This a Good Job for You? The Right (and Wrong) Fit
Who Thrives
This job suits a PA who wants continuity and hands. If you like the idea of following one patient from the decision to operate through recovery, and you are comfortable standing in an operating room for six hours, the work fits. It also suits people who are calm when a plan changes, because surgical lists change constantly.
The strongest surgical PAs tend to be organized rather than dramatic. The job rewards someone who has the imaging ready before the surgeon asks, and who notices the patient on the ward whose recovery is not tracking.
Who Should Choose Something Else
If you want to be the person who makes the operative decision, this is not the job and no amount of experience changes that. The route to that responsibility is medical school and a surgical residency, and a PA who wants it should take that path rather than hope the boundary moves.
If you want predictable hours, primary care or a clinic specialty fits better. If you dislike blood, sharp instruments, and the physical demands of standing in one place, surgical practice will wear you down regardless of how interesting the cases are.
The Comparison That Matters
Against the orthopedic PA, the difference is the patient population rather than the setting. Both work in operating rooms. The orthopedic PA owns bone and joint clinics and follows musculoskeletal injuries.
The general surgery PA covers abdominal, soft tissue, and trauma work, and spends more time on inpatients.
Against a surgeon, the difference is authority and time. The surgeon carries the technical responsibility and spends at least nine years after a bachelor’s degree getting there. The PA follows a different education and specialty-training route, then performs perioperative work within granted privileges and the surgical team’s responsibilities.
The qualified-level and specialty requirements above must also be met; a two-year PA program alone does not award the military surgical suffix.
More Information
Ask a health recruiter whether the current accession can lead to a surgical billet, and ask how the specialty fellowship selects officers this year. Then ask a surgical PA at the nearest military treatment facility what the fellowship actually involved, because the program list and the timing change.
The 42G Physician Assistant profile covers shared accession, pay, and training. The Emergency Medicine Physician Assistant and Aeromedical Physician Assistant pages cover the acute care and aircrew sides of the same field, and the Medical officer group shows how the whole community fits together.